What is VO₂max?
VO₂max is the highest rate at which you can take in, transport and use oxygen during hard exercise. It is normally expressed in millilitres of oxygen per kilogram of body mass per minute. At its simplest, it is described by the Fick equation:
V̇O₂ = Q̇ × (CₐO₂ − CᵥO₂)
Cardiac output $\dot{Q}$ is heart rate × stroke volume: how many times the heart beats, and how much blood it ejects each time. The term in brackets is oxygen extraction: arterial oxygen content minus what is left in mixed venous blood. At maximum effort, VO₂max is therefore how much blood the heart can deliver, times how much oxygen muscle can pull out of that blood.
Read that line again. Because it essentially describes many of the processes a human body can perform. VO₂max is not a mysterious longevity molecule. It is a stress test of the heart, blood, and working muscles, forced to show their capacities at the same moment.
A few details are particularly important when thinking about what the score actually represents:
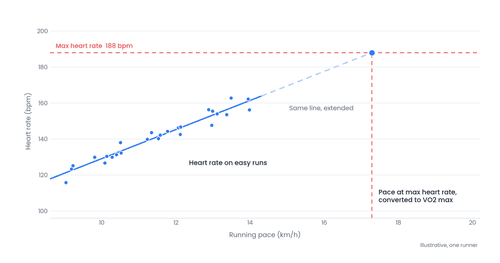
- Max HR is mostly age. Training doesn’t move it much. You do not get fitter by raising your ceiling heart rate.
- Stroke volume is where training has an impact. Plasma volume (better filling), a bigger end-diastolic volume (bigger chamber), a stronger squeeze (more muscle): more blood per beat. That is the main reason VO₂max rises in healthy people.
- Extraction is the other half (how well the muscles use oxygen). More capillaries, more mitochondria, better local blood flow. Two people can print the same VO₂max with different mixes of a big pump versus greedy muscle.
- The kg in ml/kg/min is body mass. Lose fat and the number goes up without the heart having changed. Gain muscle and it can go down while you are more robust.
So when a cohort study says “higher VO₂max, lower death rate,” it is not saying the exact number caused the years. It is saying that people whose hearts can raise output, whose blood carries oxygen efficiently, and whose muscles can use it are the people who still have reserve.
Already, VO₂max is beginning to look rather less like one thing.
Does VO₂max actually predict death, or is that just correlation?
The association between cardiorespiratory fitness and mortality is large and remarkably consistent. But it is still worth being precise about what the evidence says.
We don't have a randomised trial in which thousands of people were assigned to "raise your VO₂max" or "don't raise your VO₂max", followed for 30 years and then compared for mortality. So we shouldn't pretend that increasing VO₂max by five millilitres automatically buys a certain number of extra years of life. But equally, we shouldn't pretend the signal is weak.
Kodama and colleagues pooled 33 studies involving approximately 103,000 people. Every additional 1 MET of maximal aerobic capacity (approximately 3.5 ml/kg/min) was associated with a 13% lower risk of all-cause mortality and a 15% lower risk of coronary heart disease or cardiovascular events. People in the low-fitness category, below approximately 7.9 METs, had around 70% higher all-cause mortality than those in the high-fitness category, above approximately 10.9 METs.
That is an observational association after statistical adjustment. It is not proof that the VO₂max number itself caused the difference.
Mandsager and colleagues looked at 122,007 adults who underwent exercise treadmill testing at the Cleveland Clinic. Again, fitness and mortality moved strongly in opposite directions. Comparing the lowest fitness group with the elite fitness group produced an adjusted hazard ratio of roughly five.
What we don't know is whether the VO₂max number itself is the causal variable. Reverse causation clearly matters: early disease can reduce exercise capacity years before somebody receives a diagnosis. Confounding matters too. People who exercise regularly tend to differ from sedentary people in many other ways.
But that messiness may actually be part of the reason VO₂max is such a useful measurement. If the score reflects cardiovascular function, oxygen-carrying capacity, muscle function, body composition, habitual physical activity and the presence or absence of disease, then trying to statistically remove every one of those "confounders" begins to miss the point. Perhaps its strength is precisely that it encompasses so much.
Does getting fitter, or staying fit, change the story?
One fitness test followed by mortality decades later is interesting. Changes in fitness are more interesting.
Blair and colleagues studied 9,777 men who completed two maximal exercise tests roughly five years apart and were then followed longitudinally. The men who remained unfit had the highest mortality, while those who remained fit had the lowest. Most interestingly, men who moved from unfit to fit had around 44% lower all-cause mortality than those who remained unfit. Each additional minute of treadmill performance gained between tests was associated with roughly 8% lower mortality.
Lee and colleagues later reported something similar. Maintaining or improving cardiorespiratory fitness was associated with lower all-cause and cardiovascular mortality even after accounting for changes in BMI. Each additional MET of improvement was associated with approximately 15% lower all-cause mortality and 19% lower cardiovascular mortality.
Again, this is observational evidence. People were not randomly assigned to become fitter. But it is closer to the question we really care about: does the direction of travel matter? The evidence suggests that it does.
And this leads to a point I think gets lost when people become obsessed with attaining an enormous VO₂max. The biggest health benefit probably isn't going from 60 to 65. It is avoiding the bottom of the distribution.
What happens as we age?
VO₂max falls with age. The exact rate varies considerably depending on starting fitness, sex, body composition and, crucially, whether somebody continues training.
A useful broad estimate is somewhere around 5–10% per decade, although averages hide enormous individual variation. Rogers and colleagues found that sedentary men lost around 12% per decade, whereas master endurance athletes who continued training lost around 5.5% per decade.
Katzel and colleagues produced an even more interesting result. Over longitudinal follow-up, the endurance athletes as a group experienced a substantial decline in VO₂max, largely because many reduced their training. But the seven athletes who maintained vigorous training had essentially no significant decline. That doesn't mean training can completely stop ageing, but it does show just how much a change in training behaviour can influence the apparent age-related trajectory.
This makes me think about ageing VO₂max in two ways. The first is the intercept. If you start at 60 ml/kg/min rather than 35, you can lose quite a lot before you reach a level associated with substantial functional limitation. That reserve probably matters.
The second is the slope. At 50, 60 or 70 years old, I suspect it becomes increasingly useful to ask not simply, "What is my VO₂max?", but, "How quickly is it falling?" A person at 45 ml/kg/min whose fitness is relatively stable may tell you something very different from somebody at 50 whose fitness is declining rapidly. The trajectory might eventually be more informative than the snapshot.
And again, the mortality data point towards the same thing. The biggest difference in risk occurs towards the bottom of the fitness distribution. Moving from very low fitness to moderate fitness appears considerably more important for population health than chasing the elite tail.
So how do you train VO₂max?
This is where things become complicated. There are endless recommendations on social media about the "optimal" VO₂max workout. There is a reasonable chance that most of them are both right and wrong: right for a particular person, at a particular point in training, and wrong as a universal prescription.
This isn't drug literature. We have lots of relatively short training studies, often lasting six to twelve weeks and frequently involving young men of varying initial fitness. We have far fewer controlled studies looking at structural adaptation over months and years. And we have essentially no randomised evidence showing that one particular method of raising VO₂max leads to greater longevity than another.
So I think we need to return to the physiology. Training can improve VO₂max by increasing oxygen delivery, increasing oxygen extraction, or both. Different training stimuli may emphasise those adaptations differently. Importantly, they don't all occur on the same timescale.
Plasma volume can change relatively quickly. Mitochondrial adaptations begin rapidly but can continue accumulating. Capillary changes take time. Meaningful structural remodelling of the heart occurs over months and years. This matters when interpreting short training studies.
What does intensity do?
Helgerud and colleagues produced one of the classic studies in this area. Forty moderately trained young men performed one of four endurance-training programmes for eight weeks, with total work deliberately matched between groups.
Easy running at approximately 70% of maximum heart rate and lactate-threshold running did not significantly raise VO₂max. Short 15/15 intervals increased it by around 5.5%, while four-by-four-minute intervals at 90–95% of maximum heart rate increased it by around 7.2%. Stroke volume increased by approximately 10% in the interval groups, and the changes in VO₂max corresponded closely with changes in stroke volume.
That is persuasive evidence that high-intensity work can provide a very strong central cardiovascular stimulus. But there is an important limitation. The study deliberately matched the total amount of work performed.
That answers one useful question: for a given amount of work, which intensity provides the strongest stimulus? It does not answer another, equally important question: how should somebody distribute all of the training they can sustainably perform?
The great advantage of easy training is precisely that you can do a lot of it. You can accumulate many more minutes at an aerobic intensity than you can performing four-minute intervals at 90–95% of maximum heart rate. Anyone who has trained seriously for endurance sport knows this intuitively.
Tjønna and colleagues also produced an interesting result. Previously inactive middle-aged men performed either one four-minute high-intensity interval or four four-minute intervals, three times a week for ten weeks. VO₂max increased by roughly 10% in the one-interval group and 13% in the four-interval group.
The difference between protocols wasn't statistically significant, so this isn't proof of a saturation point. But it raises an interesting possibility: increasing the dose of high-intensity work does not necessarily produce a proportionally larger adaptation.
Meta-analyses point in broadly the same direction. When training time is constrained, interval training tends to produce a slightly greater increase in VO₂max than moderate continuous training. Milanović and colleagues reported an advantage of roughly 1.2 ml/kg/min in healthy young to middle-aged adults, while Poon and colleagues found a difference of around 1.1 ml/kg/min in middle-aged and older adults.
So intensity appears to be particularly efficient per minute. That doesn't necessarily mean it is the thing to maximise over a year.
Intensity versus volume
This is where my interpretation of the evidence becomes slightly different from some of the discussion I see around VO₂max. I think intensity is an extraordinarily efficient way to generate a large physiological stimulus in a short period of time. Volume is the stimulus you can continue accumulating.
The mitochondrial literature is a good example. Training intensity appears particularly important for mitochondrial respiratory function, whereas total training volume seems to be a major determinant of how much mitochondrial content is accumulated. Capillary adaptation also seems to respond strongly to repeated endurance work. In Daussin and colleagues' comparison of continuous and interval training, for example, both approaches improved aerobic physiology, but some peripheral adaptations differed substantially between protocols.
The most successful endurance athletes don't choose intensity or volume. They do both. Descriptive work on internationally competitive endurance athletes consistently shows that a very large proportion of training is performed at relatively low intensity, alongside a much smaller amount of genuinely hard work. Seiler's review puts the broad pattern at around 80% low-intensity sessions and 20% involving higher-intensity work.
That evidence is descriptive rather than a randomised demonstration that an 80:20 distribution is universally optimal. But it makes physiological sense. Hard training is highly stimulatory but expensive. Easy training is less stimulatory per minute but vastly more repeatable. Over weeks, months and years, that matters.
One of the most interesting studies for me is the work from Arbab-Zadeh, Howden, Levine and colleagues. Twelve previously sedentary adults trained progressively for a year towards completing a marathon. Their average VO₂max increased from approximately 40 to 49 ml/kg/min
But the cardiac adaptations didn't all happen at once. Some changes occurred relatively quickly, while structural cardiac remodelling took considerably longer. Left-ventricular cavity size changed relatively little during the first six months, with more substantial enlargement appearing later as the programme progressively added greater training volume, longer sessions and intervals.
That is interesting because an eight-week training study can only show you the adaptations that happen within eight weeks. It cannot tell you what twelve months or ten years of training produces. And that may be particularly important when thinking about longevity.
Personally, I’m fully of the opinion that the foundational changes needed for maximising your personal VO₂max have to come from large amounts of accumulated aerobic volume. High-intensity training is a potent stimulus, but one with very quickly diminishing returns.
What should different people actually do?
For somebody untrained, detrained or sitting near the bottom of the fitness distribution, almost any consistent aerobic training is likely to improve VO₂max. A relatively small amount of high-intensity work can generate remarkably large gains over eight to twelve weeks. But maintaining those gains for decades probably depends more on creating a sustainable training habit than finding the theoretically perfect interval session.
For somebody already running or cycling several times a week, introducing a new stimulus will often work. Adding intensity can produce a relatively rapid improvement. Adding volume may produce slower adaptations that can continue accumulating over a longer period.
For a well-trained endurance athlete, there is much less low-hanging fruit. At that point, hard sessions remain important, but they sit on top of a much larger volume of aerobic work. The exact ratio is individual, but elite endurance training is generally characterised by a large amount of lower-intensity work and a relatively small amount of very hard work.
There are also potentially important sex differences that we don't fully understand, not least because so much classic exercise physiology research was conducted predominantly in men. In the year-long training study from Howden and colleagues, the women (admittedly only five of them) appeared to plateau earlier than the men in VO₂max, left-ventricular mass and wall thickness, although left-ventricular end-diastolic volume increased similarly in both sexes.
A later systematic review and meta-analysis also found smaller increases in left-ventricular end-diastolic volume in women than in men, while increases in stroke volume were significant in the pooled male studies but not in the female studies. Age appeared to blunt several cardiac adaptations more strongly in women. More recent evidence continues to suggest that some sex differences exist, although exactly which adaptations differ remains an active area of research.
Older adults are another group where I think simple prescriptions are dangerous. Both high-intensity interval training and moderate continuous training can improve VO₂max. The best programme is probably the one that provides sufficient stimulus while remaining sustainable, recoverable and safe enough to perform repeatedly.
Which sounds boring. But ageing well is probably quite a boring training problem.
Back to measurement
All of this brings me back to where I started. Why does VO₂max predict health so well?
I think part of the answer is that the number compresses an enormous amount of physiology into one measurement. To have a high VO₂max, you generally need an effective cardiovascular system, enough haemoglobin to carry oxygen, muscles capable of extracting and using it, and enough functioning muscle mass to do the work. Your lungs, heart, blood, circulation and muscles all have to function together under stress.
Then there is another layer. A high VO₂max often reflects years of regular physical activity. That physical activity creates other adaptations that don't sit neatly inside the Fick equation: improved glucose regulation, healthier body composition, stronger muscle and bone, better vascular function and greater physical reserve.
And then there are the things that travel alongside an active life. People who exercise regularly may sleep differently, eat differently, maintain more muscle and remain more physically capable as they age. Some of these things contribute to the VO₂max measurement. Some result from the training that created it. Some are correlated with it. And some may simply tell us that disease has not yet substantially impaired the system.
So perhaps VO₂max predicts health so well partly because it is a wonderfully messy variable. It isn't one isolated biological mechanism. It is an integrated stress test of a large part of the human body.
And that changes how I think we should use it. Rather than obsessing about whether your number is 48, 52 or 55, I think there are two additional questions worth asking.
Firstly, what is producing your score? Is it being driven primarily by cardiac output, oxygen-carrying capacity, peripheral extraction, body composition, muscle mass, or some combination of all of them? Understanding that potentially tells you much more about where there is room to improve.
Secondly, where is it going? Where are you relative to people of your age? Is your VO₂max increasing, stable or decreasing? And, perhaps most importantly as you get older, is it falling faster or slower than you would expect?
I started looking into this because I was slightly sceptical about the growing obsession with VO₂max as a longevity number. I've ended up more convinced of its value. But not because I think there is anything magical about a particular number of millilitres of oxygen. I think VO₂max is useful because it isn't really one number at all. It is a summary of an enormous amount of physiology.
And the really interesting part may be understanding what is underneath it and which direction it is heading.
References
- Arbab-Zadeh A, Perhonen M, Howden E, et al. Cardiac remodeling in response to 1 year of intensive endurance training. Circulation. 2014;130(24):2152–2161.
DOI: https://doi.org/10.1161/CIRCULATIONAHA.114.010775 - Bishop DJ, Botella J, Granata C. CrossTalk opposing view: Exercise training volume is more important than training intensity to promote increases in mitochondrial content. Journal of Physiology. 2019;597(16):4115–4118.
DOI: https://doi.org/10.1113/JP277634 - Blair SN, Kohl HW III, Barlow CE, Paffenbarger RS Jr, Gibbons LW, Macera CA. Changes in physical fitness and all-cause mortality: a prospective study of healthy and unhealthy men. JAMA. 1995;273(14):1093–1098.
DOI: https://doi.org/10.1001/jama.1995.03520380029031 - Daussin FN, Zoll J, Dufour SP, et al. Effect of interval versus continuous training on cardiorespiratory and mitochondrial functions: relationship to aerobic performance improvements in sedentary subjects. American Journal of Physiology-Regulatory, Integrative and Comparative Physiology. 2008;295(1):R264–R272.
DOI: https://doi.org/10.1152/ajpregu.00875.2007 - Diaz-Canestro C, Montero D. The impact of sex on left ventricular cardiac adaptations to endurance training: a systematic review and meta-analysis. Sports Medicine. 2020;50(8):1501–1513.
DOI: https://doi.org/10.1007/s40279-020-01294-9 - Granata C, Jamnick NA, Bishop DJ. Training-induced changes in mitochondrial content and respiratory function in human skeletal muscle. Sports Medicine. 2018;48(8):1809–1828.
DOI: https://doi.org/10.1007/s40279-018-0936-y - Helgerud J, Høydal K, Wang E, et al. Aerobic high-intensity intervals improve VO₂max more than moderate training. Medicine & Science in Sports & Exercise. 2007;39(4):665–671.
DOI: https://doi.org/10.1249/mss.0b013e3180304570 - Howden EJ, Perhonen M, Peshock RM, et al. Females have a blunted cardiovascular response to one year of intensive supervised endurance training. Journal of Applied Physiology. 2015;119(1):37–46.
DOI: https://doi.org/10.1152/japplphysiol.00092.2015 - Katzel LI, Sorkin JD, Fleg JL. A comparison of longitudinal changes in aerobic fitness in older endurance athletes and sedentary men. Journal of the American Geriatrics Society. 2001;49(12):1657–1664.
DOI: https://doi.org/10.1046/j.1532-5415.2001.t01-1-49276.x - Kodama S, Saito K, Tanaka S, et al. Cardiorespiratory fitness as a quantitative predictor of all-cause mortality and cardiovascular events in healthy men and women: a meta-analysis. JAMA. 2009;301(19):2024–2035.
DOI: https://doi.org/10.1001/jama.2009.681 - Lee DC, Sui X, Artero EG, et al. Long-term effects of changes in cardiorespiratory fitness and body mass index on all-cause and cardiovascular disease mortality in men: the Aerobics Center Longitudinal Study. Circulation. 2011;124(23):2483–2490.
DOI: https://doi.org/10.1161/CIRCULATIONAHA.111.038422 - Mandsager K, Harb S, Cremer P, Phelan D, Nissen SE, Jaber W. Association of cardiorespiratory fitness with long-term mortality among adults undergoing exercise treadmill testing. JAMA Network Open. 2018;1(6):e183605.
DOI: https://doi.org/10.1001/jamanetworkopen.2018.3605 - Milanović Z, Sporiš G, Weston M. Effectiveness of high-intensity interval training and continuous endurance training for VO₂max improvements: a systematic review and meta-analysis of controlled trials. Sports Medicine. 2015;45(10):1469–1481.
DOI: https://doi.org/10.1007/s40279-015-0365-0 - Montero D, Diaz-Cañestro C, Lundby C. Endurance training and VO₂max: role of maximal cardiac output and oxygen extraction. Medicine & Science in Sports & Exercise. 2015;47(10):2024–2033.
DOI: https://doi.org/10.1249/MSS.0000000000000640 - Poon ETC, Wongpipit W, Ho RST, Wong SHS. Interval training versus moderate-intensity continuous training for cardiorespiratory fitness improvements in middle-aged and older adults: a systematic review and meta-analysis. Journal of Sports Sciences. 2021;39(17):1996–2005.
DOI: https://doi.org/10.1080/02640414.2021.1912453 - Rogers MA, Hagberg JM, Martin WH III, Ehsani AA, Holloszy JO. Decline in VO₂max with aging in master athletes and sedentary men. Journal of Applied Physiology. 1990;68(5):2195–2199.
DOI: https://doi.org/10.1152/jappl.1990.68.5.2195 - Ross R, Blair SN, Arena R, et al. Importance of assessing cardiorespiratory fitness in clinical practice: a case for fitness as a clinical vital sign: a scientific statement from the American Heart Association. Circulation. 2016;134(24):e653–e699.
DOI: https://doi.org/10.1161/CIR.0000000000000461 - Seiler S. What is best practice for training intensity and duration distribution in endurance athletes? International Journal of Sports Physiology and Performance. 2010;5(3):276–291.
DOI: https://doi.org/10.1123/ijspp.5.3.276 - Tjønna AE, Leinan IM, Bartnes AT, et al. Low- and high-volume of intensive endurance training significantly improves maximal oxygen uptake after 10-weeks of training in healthy men. PLoS ONE. 2013;8(5):e65382.
DOI: https://doi.org/10.1371/journal.pone.0065382